


Good AMH Level for IVF: What Your Result Means?
By Dr. Firuza Parikh · Published: August 2024 · Last updated: October 2026 · Medically reviewed
Quick Answer
A “good” AMH for IVF is above 1.0 ng/mL (7.1 pmol/L). Below 0.5 ng/mL (3.6 pmol/L) is very low — but not a reason to rule out IVF.
AMH predicts how many eggs your ovaries can produce — not whether those eggs are healthy.
Age drives egg quality; AMH drives egg quantity.
Key Takeaways
- AMH reflects egg quantity, not egg quality: it counts the follicles available, not whether the eggs inside them are chromosomally normal.
- No absolute minimum for IVF: even AMH below 0.5 ng/mL does not rule out a successful cycle — protocol adjustments and close monitoring compensate for fewer eggs.
- 31% of “poor responders” beat expectations: 31% of women with AMH <1.2 ng/mL produced more than 4 eggs, with blastocyst quality exceeding the poor-responder average.
- Indian lab unit confusion is real: SRL and Metropolis report AMH in pmol/L. Divide by 7.14 to get ng/mL. A result of 14.3 pmol/L = 2.0 ng/mL — perfectly normal.
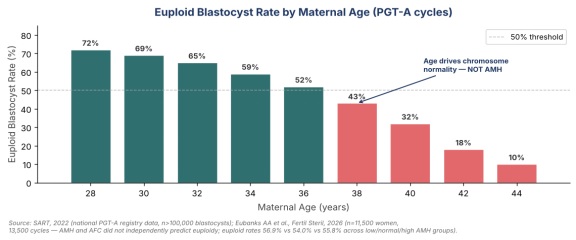
- Age drives embryo health, not AMH: euploid blastocyst rates fall from ~72% at age 28 to ~10% at age 44 regardless of AMH. A 32-year-old with low AMH produces fewer eggs but most will be chromosomally normal.
- Your specialist’s read of your full clinical picture — AMH, AFC, age, hormone panel — always outweighs any single number, including AMH.
On this Page
- What AMH measures — and what it does not
- AMH reference ranges: reading your result
- AMH and age: why both numbers matter together
- AMH and your embryo’s chromosomes: the 2026 paradigm shift
- Reading your AMH report: the unit problem Indian patients miss
- Before your AMH test: 5 things that affect the reading
- How AMH shapes your IVF stimulation protocol
- Questions patients actually ask
- Can I get pregnant naturally with low AMH?
- AMH after 40: what your result means when time is short
- Frequently asked questions
What AMH Measures — and What It Does Not?
AMH is produced by the granulosa cells surrounding small, growing follicles, making it a reliable proxy for the size of your remaining egg pool. Unlike FSH or oestradiol, AMH stays stable across the menstrual cycle and between labs on the same assay — so it can be tested on any day. A single blood draw gives your doctor a clear window into ovarian reserve.
What it cannot tell you is whether the eggs inside those follicles are chromosomally intact. A follicle with a low-quality egg and one with a high-quality egg are counted identically by AMH. That distinction is governed primarily by your age — not your ovarian reserve score.
Because of this, AMH is the single best predictor of how many eggs you will retrieve at egg collection during IVF — but it is a quantity predictor, not a quality predictor.
AMH Reference Ranges: Reading Your Result
The table below gives the four clinically used ranges and what each typically means for IVF planning.
AMH (ng/mL) | Level | Eggs Expected | IVF Outlook | Typical Action |
> 3.5 | High / PCOS | 15–25+ | Strong response; OHSS risk | Low-dose protocol; freeze-all cycle common; OHSS prevention priority |
1.0–3.5 | Normal | 8–15 | Good; standard protocol | Standard stimulation; proceed with confidence |
0.5–1.0 | Low | 3–7 | Manageable with adjustment | Higher gonadotropin dose; close monitoring; PGT-A to identify euploid embryos |
< 0.5 | Very Low (DOR) | 1–4 | Lower per-cycle rate; possible with right protocol | High-dose protocol; consider natural or mini-IVF; egg donation if multiple cycles fail. Do not delay — age is co-factor |
Source: La Marca A et al., Hum Reprod Update, 2010; POSEIDON Group, Hum Reprod Open, 2016.
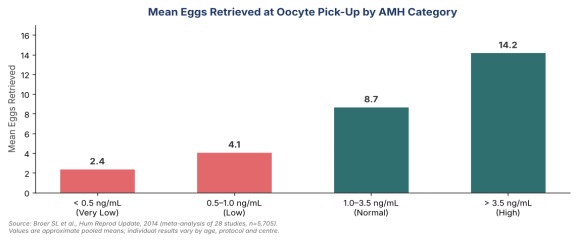
Source: Broer SL et al., Hum Reprod Update, 2014.
AMH and Age: Why Both Numbers Matter Together?
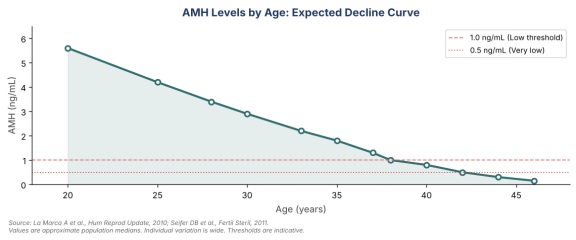
AMH falls steadily with age, but the decline is not linear — and the point at which it crosses key thresholds tells your doctor far more than either number alone.
The chart below traces population median AMH across reproductive age. Notice that the “Low” threshold (1.0 ng/mL) is typically crossed around age 37–38, and the “Very Low” threshold (0.5 ng/mL) around age 40–42. But there is enormous individual variation: some women at 30 have the reserve of a 40-year-old, and some 40-year-olds have the reserve of a 35-year-old.
Source: La Marca A et al., Hum Reprod Update, 2010; Seifer DB et al., Fertil Steril, 2011.
Age-banded AMH reference: approximate median values
Age bracket | Median AMH (ng/mL) | Typical egg response | Egg quality note |
25–29 | 4.2–5.6 | 15–20 eggs | Euploid rate ~65–72% (SART PGT-A) |
30–34 | 2.9–4.2 | 10–16 eggs | Euploid rate ~55–65% |
35–37 | 1.8–2.9 | 8–14 eggs | Euploid rate ~45–55%; PGT-A increasingly valuable |
38–40 | 0.8–1.8 | 4–10 eggs | Euploid rate ~30–45%; age now a primary concern |
41–43 | 0.3–0.8 | 2–6 eggs | Euploid rate ~15–30%; consider PGT-A for every blastocyst |
44+ | < 0.3 | 1–3 eggs | Euploid rate ~10%; egg donation often discussed |
Source: Approximate pooled medians from La Marca A et al. (2010); euploid rates from SART PGT-A registry 2022.
Source: Tal R et al., Fertil Steril, 2015; Nelson SM et al., Fertil Steril, 2009.
AMH and Your Embryo's Chromosomes: The 2026 Paradigm Shift
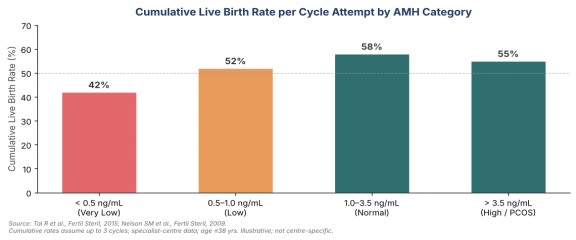
Most AMH articles imply that a higher score means better IVF outcomes overall. The largest study ever conducted on this question says otherwise.
In 2026, Eubanks et al. published findings from 11,500 women across 13,500 IVF cycles — the most comprehensive analysis yet of whether AMH predicts embryo chromosomal health. Their conclusion: AMH and AFC do not independently predict embryo euploidy.
Euploid (chromosomally normal) blastocyst rates across AMH groups were virtually identical:
- Low AMH (< 1.2 ng/mL): 9% euploid blastocysts
- Normal AMH (1.2–3.5 ng/mL): 0% euploid blastocysts
- High AMH (> 3.5 ng/mL): 8% euploid blastocysts
The numbers are essentially identical. What actually varied was the total blastocyst yield — higher AMH women produced more blastocysts, so they had more chances to find a euploid one. But each individual blastocyst had the same chance of being chromosomally normal regardless of AMH.
Source: SART PGT-A registry 2022; Eubanks et al., Fertil Steril, 2026.
What this means for you: if you are 33 with AMH of 0.6 ng/mL, you will likely retrieve fewer eggs than a 33-year-old with AMH of 2.8 — but the eggs you do retrieve have the same chromosomal quality. The focus should be on retrieving enough eggs to find one or two euploid blastocysts — which is exactly what modern high-dose protocols are designed to achieve.
The "Unexpected Good Responder" — Why AMH Should Not Be an Absolute Discriminator?
A 2024 study from the Kraków IVF Unit found that 202 women — 31% of the entire low-AMH group — produced more than 4 mature eggs at retrieval. Their blastocyst quality (46% euploidy rate) significantly exceeded that of classic poor responders (26%).
The researchers concluded that AMH should not be used as an “absolute discriminator” for cancelling cycles or redirecting patients to egg donation. Ovarian reserve testing should guide, not decide.
What this means for you: if a low AMH result has been used to discourage you from IVF, seek a second opinion. At FertilTree, we assess AMH alongside AFC, age, FSH, and individual stimulation history before making any recommendation about IVF treatment in Mumbai.
Reading Your AMH Report: The Unit Problem Indian Patients Miss
If your Indian lab report shows a number in pmol/L, you are not reading the same scale as a result in ng/mL — and directly comparing them is one of the most common sources of unnecessary panic or false reassurance.
Major Indian diagnostic chains — SRL Diagnostics, Metropolis Healthcare, and many hospital labs — run AMH on the Beckman Coulter Access AMH (Gen II) assay, which reports results in picomoles per litre (pmol/L). Most international and specialist fertility clinic ranges are published in nanograms per millilitre (ng/mL).
Conversion formula: ng/mL × 7.14 = pmol/L (or: pmol/L ÷ 7.14 = ng/mL)
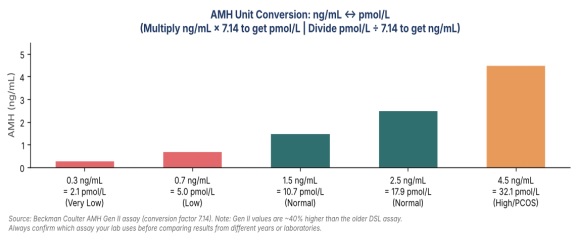
Source: Beckman Coulter Gen II Access AMH package insert.
Quick conversion reference:
Your lab reports (pmol/L) | Equivalent (ng/mL) | Clinical level | What it means |
< 3.6 | < 0.5 | Very Low (DOR) | Discuss protocol options early |
3.6–7.1 | 0.5–1.0 | Low | Adjusted protocol; specialist assessment |
7.1–25.0 | 1.0–3.5 | Normal | Standard IVF expected response |
> 25.0 | > 3.5 | High / PCOS territory | OHSS prevention; low-dose protocol |
Conversion based on Beckman Coulter Access AMH (Gen II) assay.
How Much Does an AMH Test Cost in India?
In India, the cost of an Anti-Mullerian Hormone (AMH) blood test typically ranges from ₹1,400 to ₹2,500 at most standard private diagnostic centers. Prices fluctuate depending on the city, the type of laboratory, and whether you opt for home sample collection.
- Estimated Price Breakdown:
- Standard Private Diagnostic Labs:₹1,400 – ₹2,500
- Premium Hospital Labs & Fertility Clinics:₹2,500 – ₹3,500
- Government Facilities:₹300 – ₹500
Key Testing Guidelines for Patients:
- No Prescription Required:In most Indian states, patients can book an AMH test directly with a diagnostic center without needing a doctor’s referral.
- Flexible Timing: The blood draw can be done on any day of the menstrual cycle. Unlike other fertility hormones (such as FSH or oestradiol), AMH levels remain stable and do not fluctuate throughout the month.
- Measurement Units:Depending on the laboratory’s specific equipment, your results may be reported in either ng/mL or pmol/L. You can use a standard conversion table to compare them, or simply provide the lab report to your specialist for interpretation.
Cost vs. Quality:
Paying a premium rate at a high-end hospital does not mean a different or better hormone is being measured. The test evaluates the exact same AMH levels; the price variation is strictly due to the laboratory’s chosen assay technology, location, and facility fees.
The Gen II vs DSL Assay Difference — Why Your 2020 and 2025 Results Cannot Be Directly Compared?
If you had an AMH test before 2014 using the older Immunotech/Beckman DSL assay and a more recent test using the Gen II assay, the Gen II will read approximately 30–40% higher for the same serum sample. A “rise” in AMH from one result to another may simply reflect an assay change, not a real improvement in ovarian reserve.
The practical rule: always check which assay your lab used before comparing AMH results from different years or different laboratories. Ask your lab or fertility clinic to confirm.
Practical takeaway: bring all previous AMH reports to your consultation. At Jaslok-FertilTree International Fertility Centre, we routinely check assay history before interpreting trend data.
Before Your AMH Test: 5 Things That Affect the Reading
AMH is one of the most stable reproductive hormones — but “stable” does not mean immovable.
Before you receive your result, five modifiable factors can shift your AMH reading enough to change your clinical category:
Factor | Effect on AMH | What to do |
Oral contraceptive pills (OCP) | Reduces by 10–30% | Test 2–4 weeks after stopping OCPs |
Vitamin D deficiency | May reduce AMH 10–20% | Check 25-OH-D; supplement if < 30 ng/mL |
Lab assay type | Gen II reads ~35% higher than DSL | Confirm assay used; note for comparisons |
Recent illness / major surgery | Temporary suppression (mechanism unclear) | Retest after full recovery (4–6 weeks) |
BMI and smoking | High BMI / smoking: may lower AMH | Report current BMI and smoking status to lab/clinic |
Sources as cited in table. Effects are approximate and reversible where noted.
How AMH Shapes Your IVF Stimulation Protocol?
AMH is the primary metric used by IVF clinics to set your starting gonadotropin dose — too little and you under-stimulate; too much and you risk OHSS.
The POSEIDON (Patient-Oriented Strategies Encompassing IndividualiseD Oocyte Number) Group published standardised dose-guidance in 2016 (Hum Reprod Open). The chart below shows typical starting doses by AMH category:
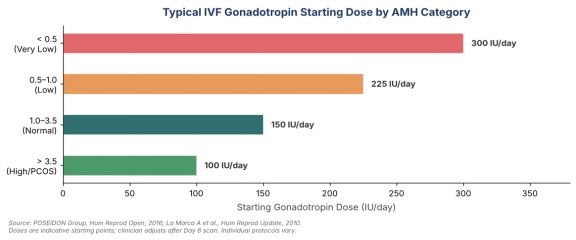
Source: POSEIDON Group, Hum Reprod Open, 2016.
AMH vs AFC vs FSH: Which test predicts ovarian response best?
Feature | AMH | AFC (Antral Follicle Count) | FSH (Day 3) |
What it measures | Granulosa cell output — ovarian reserve proxy | Follicles 2–10 mm visible on ultrasound | Pituitary signal — how hard brain works to recruit eggs |
Cycle-day dependency | None — test any day | Day 2–5 best | Day 2–4 only |
Sensitivity for poor response | 76% (La Marca 2010) | 72% | 54% |
Specificity for poor response | 95% | 96% | 81% |
Lab variability | Assay-dependent (Gen II vs DSL) | Operator-dependent | Low intra-lab variability |
Predicts euploidy? | No (Eubanks 2026) | No (Eubanks 2026) | No |
Source: La Marca A et al., Hum Reprod Update, 2010; Eubanks et al., Fertil Steril, 2026.
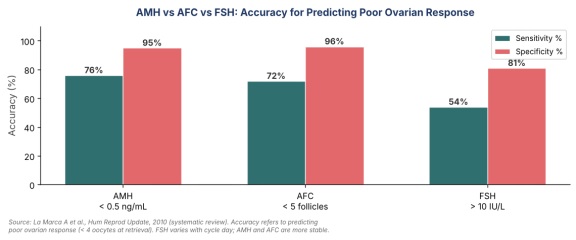
Source: La Marca A et al., Hum Reprod Update, 2010 (systematic review).
Questions Patients Actually Ask
- “My AMH is 0.3 ng/mL and I’m 38. Is IVF still worth trying?”
Yes — with caveats. The question is whether you can produce even one euploid embryo. With aggressive stimulation and PGT-A, the answer is often yes. The conversation your specialist needs to have with you is about realistic cycle numbers, not whether to try.
- “Can supplements increase my AMH?”
CoQ10, DHEA and melatonin are commonly discussed. CoQ10 has the most plausible mechanistic rationale, but clinical trials to date are small and heterogeneous. No supplement has been shown in a large RCT to significantly raise measured AMH. Vitamin D correction restores a suppressed reading, not a genuinely depleted reserve. Discuss with your specialist before starting.
- “I’m 29 with very high AMH (5.8 ng/mL). Does that mean I should delay fertility?”
High AMH tells you your reserve is robust now — it does not tell you how fast it will decline. Egg freezing before 32 typically yields a higher euploid rate per egg and more flexibility. High AMH is a reason to plan, not to postpone indefinitely.
- “My report is in pmol/L — how do I know if I’m normal?”
Divide by 7.14. Normal range = 7.1–25.0 pmol/L (= 1.0–3.5 ng/mL). See the conversion table above, or bring your report to your FertilTree consultation and we will walk through it with you.
A Cause Worth Knowing About in India: Genital Tuberculosis and AMH
Genital tuberculosis (TB) is a significant but underdiagnosed cause of diminished ovarian reserve in the Indian subcontinent. Unlike blocked fallopian tubes, genital TB can directly damage ovarian tissue, leading to an AMH that appears disproportionately low for the patient’s age. If your AMH is unexpectedly very low and you have a history of pulmonary TB or are at risk, ask your specialist to rule out genital TB through CBNAAT endometrial sampling before attributing low AMH to natural reserve decline alone.
What this means for you: at FertilTree, patients from Mumbai and across India presenting with unexplained low AMH routinely undergo genital TB screening as part of our fertility assessment protocol.
Can I Get Pregnant Naturally With Low AMH?
Yes — and this is one of the most important things to know about AMH: it is a test designed for IVF planning, not a measure of your natural fertility per cycle.
AMH estimates the size of your total egg pool. But each month, you release just one egg (usually) — and that single egg does not “know” what your AMH score is. The hormone does not block ovulation or prevent fertilisation.
Two large studies have confirmed this directly. Steiner et al. found that women with low AMH and women with normal AMH had virtually identical 12-month conception rates when age was accounted for. Brodin et al. similarly found AMH was not independently associated with time to natural conception after adjusting for age.
What low AMH does affect naturally: it shortens your fertile horizon. A smaller egg pool means fewer years before menopause — so the urgency is about timing, not about your monthly ovulation. If your AMH is low at 28, you may have 5–7 fewer fertile years than expected; if low at 36, the window may already be narrowing. In both cases: do not delay.
Practical takeaway for natural conception with low AMH:
- Do not wait: each month counts more with a smaller reserve.
- Track ovulation: LH strips or an ultrasound-confirmed cycle confirms you are ovulating and when.
- Consider egg freezing in parallel: if not ready to conceive immediately, egg freezing in Mumbaibanked before further reserve decline gives you future options at today’s egg quality.
- Reassurance: a low AMH at 30 is not the same as infertility. It is a signal to plan carefully — not to panic.
Worth saying plainly: low AMH does not mean you cannot conceive naturally. It means the window may be shorter than average, and that a specialist conversation sooner rather than later is worth having.
AMH After 40: What Your Result Means When Time is Short?
At 40, the conversation shifts. Your AMH still matters — but your age is now the bigger number in the room.
By age 40, population median AMH is typically 0.5–0.9 ng/mL. By 42, it is often below 0.5 ng/mL. But here is what matters more: the chance that any given egg is chromosomally normal — what doctors call the “euploid rate” — is now around 30–40% (age 40–42) and falls to 15–25% by age 43–44, regardless of AMH level.
This means a 42-year-old with AMH of 2.0 ng/mL has a higher egg yield than a 42-year-old with AMH of 0.4 ng/mL — but both have the same ~35% per-egg chance of euploidy. Higher AMH at 40+ means more attempts to find the normal embryo, not healthier eggs.
AMH at 40+ | Likely egg yield | Recommended approach | What to discuss with specialist |
> 1.0 ng/mL | 8–12 eggs | Own-egg IVF with PGT-A; consider banking blastocysts before 42 | Number of euploid embryos expected; time to attempt |
0.5–1.0 ng/mL | 4–8 eggs | Own-egg IVF; may need 2–3 cycles for 1 euploid embryo; mini-IVF alternative | Cumulative euploid embryo rate across cycles; egg donation timeline if needed |
< 0.5 ng/mL | 1–3 eggs | Own eggs still possible (POSEIDON high-dose); egg donation offers the most predictable outcome over 40 | Success rates with own vs donor eggs at your specific age; emotional readiness |
Source: SART PGT-A registry 2022; POSEIDON Group, Hum Reprod Open, 2016; Eubanks et al., Fertil Steril, 2026.
Egg donation over 40: if AMH is very low and multiple own-egg cycles have not produced a euploid embryo, donor eggs with a proven euploid embryo transfer can achieve live birth rates of 40–50% per transfer regardless of the recipient’s age. This is not giving up — it is choosing the most effective path given the biology.
What this means for you at 40+: do not interpret a relatively normal AMH as a reason to wait. And do not interpret a low AMH as reason to abandon your own eggs without trying. The right call depends on your specific AFC, your cycle history, and a conversation with your specialist about realistic embryo expectations over a defined number of cycles. At FertilTree, that conversation is the first thing we have.
Bottom Line
AMH tells you how many eggs to expect — not how healthy they are, and not whether IVF will work. What actually determines embryo quality is your age. A low AMH result at 32 is very different from a low AMH result at 42, and a result in pmol/L from an Indian lab is not lower than a result in ng/mL — it is just a different unit. The 2026 Eubanks data confirm that even women with low AMH can produce chromosomally normal embryos at the same rate as women with high AMH. The number that matters most is how many euploid blastocysts you end up with — and that question is best answered by an individualised plan, not a single blood test.
Frequently Asked Questions
What is the minimum AMH level needed to attempt IVF?
There is no absolute minimum. Even AMH below 0.5 ng/mL does not rule out a successful cycle — protocol adjustments and close monitoring compensate for fewer eggs. Your specialist will assess AFC, age, and hormone levels alongside AMH. Learn more about IVF at FertilTree
Does low AMH mean poor egg quality?
No — this is one of the most common misunderstandings about AMH. The test reflects egg quantity, not chromosomal quality. A 2026 study found euploid rates were virtually identical across all AMH groups. Age is the primary driver of egg quality.
My lab report shows pmol/L, not ng/mL — what does that mean?
Many Indian labs report AMH in pmol/L using the Beckman Coulter Gen II assay. Divide your pmol/L result by 7.14 to convert to ng/mL. For example, 14.3 pmol/L = 2.0 ng/mL (normal range). See the conversion table in the “Unit Problem” section above, or book a consultation and we will interpret it for you.
Can I get pregnant naturally if my AMH is low?
Yes — AMH does not predict your natural fertility per menstrual cycle. Two large studies found natural conception rates were virtually identical in women with low and normal AMH once age was accounted for. Low AMH shortens your fertile horizon overall — so the advice is “do not delay”, not “you cannot conceive.” Explore fertility options at FertilTree.
MEDICALLY REVIEWED BY
Dr. Firuza Parikh
MD, PhD, Director, Jaslok-FertilTree International Fertility Centre
Diminished ovarian reserve and the interpretation of AMH in the context of IVF planning are among the most frequent clinical conversations Dr. Parikh has with patients referred to FertilTree from across India and internationally. She trained in IVF and Reproductive Endocrinology at Yale University School of Medicine under Dr. Alan DeCherney, established one of India’s first private-hospital IVF centres at Jaslok Hospital in 1989, and delivered South-East Asia’s first ICSI baby in 1994. Over more than three decades in reproductive medicine, she and her team have helped deliver more than 20,000 babies for patients from over 60 countries.