

What Causes Infection in Sperm?
By Dr. Firuza Parikh · Published: November 2023 · Last updated: October 2026 · Medically reviewed
Quick Answer
Most sperm infections start as a urinary tract infection, a sexually transmitted infection, or inflammation of the prostate or epididymis that reaches the semen. Bacteria like E. coli trigger inflammation and oxidative stress that can impair sperm movement and function — but a semen culture catches it, and antibiotics usually clear it.
An estimated 15% of male infertility cases trace back to an infection somewhere in the reproductive tract — and most of them are treatable.
It almost always starts in one of three places: a urinary tract infection that spreads backward, a sexually transmitted infection, or inflammation in the prostate or epididymis. Here’s exactly where it comes from, how to tell your semen is affected, and what actually clears it.
Key takeaways
- ~15% of male infertility involves infection: A recent clinical review estimates male genital tract infection accounts for about 15% of male infertility cases.
- It’s usually silent: Discomfort, discharge, or pain on ejaculation can occur, but many infections cause no symptoms at all and are only caught on a semen analysis or culture.
- The damage is mechanical, not just presence: Research shows bacteria directly bind to and immobilise sperm, while the body’s own immune response floods semen with damaging reactive oxygen species.
- coli is the most common culprit: Lab research on E. coli-derived sperm-immobilising and sperm-agglutinating factors helps explain why this single organism shows up so often in infected semen samples.
- Most cases are treatable: A targeted antibiotic course, often with simultaneous treatment for your partner, clears the large majority of bacterial causes — and a repeat semen analysis confirms it worked.
- Self-medicating first makes it worse, not better: A 2024 Delhi study found 35% of adults self-medicate with antibiotics, and 75% of those bought them straight from a pharmacy with no prescription — exactly what makes a later culture result unreliable.
- Your own test results decide the plan: A semen culture and your specialist’s interpretation of it always outweigh any general guide, including this one.
On this page
- How Does a Sperm Infection Actually Happen?
- Where Does the Infection Originate?
- What Can Infected Semen Look Like?
- Risk Factors, Organised by Type
- Symptoms: Why Are Most Infections Silent?
- How Is a Sperm Infection Diagnosed?
- Can It Be Treated?
- The India-Specific Risk: Self-Medicating Before a Culture Is Done
- Prevention: What Actually Helps?
- Questions Patients Actually Ask
- Frequently Asked Questions
How Does a Sperm Infection Actually Happen?
Bacteria don’t just sit passively in semen — they actively interfere with sperm. A 2022 review in Open Life Sciences describes three mechanisms working together: direct bacterial adhesion that clumps and immobilises sperm, toxin release that damages the sperm membrane, and an immune response that floods the semen with white blood cells and reactive oxygen species. That last part matters most for fertility — oxidative stress from the body’s own immune response often does more damage to sperm DNA and motility than the bacteria themselves.
Escherichia coli is the single most-studied culprit. Lab research on E. coli-derived “sperm immobilisation factor” and “sperm agglutinating factor” helps explain why this one organism shows up disproportionately often in infected semen samples, even though dozens of bacteria, viruses, and fungi can technically cause a sperm infection.
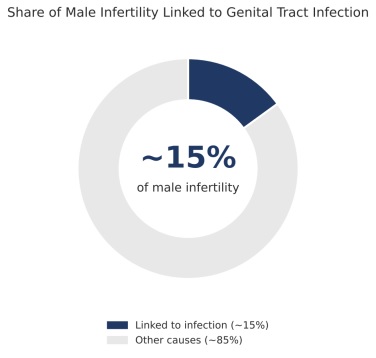
Chart 1 — Share of Male Infertility Linked to Infection
Most articles on this topic stop at “can reduce fertility” without saying by how much. A 2018 meta-analysis pooling 18 studies — 5,797 healthy men against 3,986 men with bacteriospermia — put real numbers on it: Journal of Family and Reproductive Health found statistically significant drops in sperm concentration, total count, progressive motility, normal morphology, and live sperm percentage in men with bacteriospermia — and the effect held even in men with no symptoms at all, which is exactly why screening matters more than waiting to feel something.
Semen Parameter | Effect of Bacteriospermia | Statistical Significance |
Sperm concentration | -27.06 (mean difference) | Significant decrease |
Total sperm count | -15.12 (mean difference) | Significant decrease |
Progressive motility | -12.81 (mean difference) | Significant decrease |
Normal morphology | -5.43 percentage points | Significant decrease |
Live sperm (viability) | -4.39 percentage points | Significant decrease |
Total motility | -3.64 (mean difference) | Significant decrease |
Semen pH | +0.03 (mean difference) | Significant increase |
Total semen volume | +0.02 (mean difference) | Not significant |
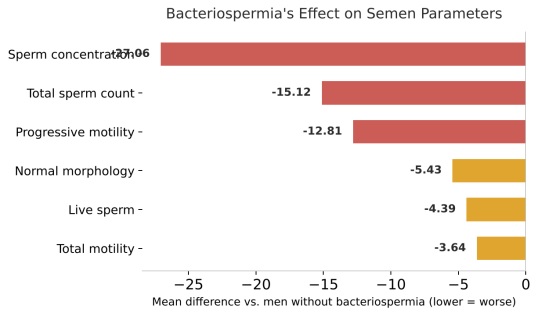
Chart 1b — Bacteriospermia’s Effect on Semen Parameters
Where Does the Infection Originate?
The bacteria responsible almost always start in one of two places: the patient’s own urinary tract, or a partner, via unprotected sexual contact. From there, infection can settle in several different sites along the reproductive tract — each with a slightly different name and a slightly different cause.
Source | What’s Actually Happening | What To Do |
Sexually transmitted infection (STI) | Chlamydia or gonorrhoea passed through unprotected sex | See a specialist promptly |
Urinary tract infection (UTI) | Bacteria in the urinary tract spreading into the reproductive system | See a specialist promptly |
Prostatitis | Inflammation or infection of the prostate gland | See a specialist promptly |
Epididymitis | Infection or inflammation of the tube that stores and carries sperm | See a specialist promptly |
Orchitis | Inflammation or infection of the testicles themselves | See a specialist promptly |
Balanitis | Infection or inflammation of the foreskin or head of the penis | Usually manageable, get it checked |
Varicocele | Enlarged scrotal veins causing overheating, not infection itself, but a common co-factor | Usually manageable, get it checked |
Poor hygiene or injury/trauma | Introduces bacteria or raises risk without a specific diagnosis | Modifiable with care |
Obstructed reproductive ducts | Blockages that let bacteria accumulate and multiply | Usually manageable, get it checked |
Source: clinical categorisation based on Rivero MJ et al., Current Opinion in Urology, 2023.
Which cause is most likely actually shifts with age — a distinction most general articles skip entirely. A clinical review in American Family Physician puts it plainly: in sexually active men aged 14 to 35, epididymitis is most often chlamydia or gonorrhoea; past 35, it’s usually enteric bacteria reflux-ing up from the urinary tract, often because of an enlarged prostate narrowing normal flow. Beyond chlamydia and gonorrhoea, Mycoplasma genitalium and Trichomonas vaginalis are increasingly recognised sexually transmitted causes of reduced sperm motility in their own right.
“Prostatitis” in the table above also isn’t one thing. Urologists classify it into four distinct types — acute bacterial, chronic bacterial, chronic pelvic pain syndrome (inflammatory but not bacterial), and asymptomatic inflammatory prostatitis — and only the first two respond to antibiotics the way most patients expect. Which type you have changes the treatment plan entirely, which is why a urology referral, not a generic antibiotic course, is the right next step for persistent prostatitis symptoms.
What Can Infected Semen Look Like?
Appearance alone never confirms an infection, but a few patterns are common enough to be worth knowing — and worth getting tested rather than self-diagnosed.
Appearance | Likely Explanation | Next Step |
Yellow-tinged semen | Leftover urine mixing with semen, or an excess of white blood cells (leukocytospermia / pyospermia) | Get a semen culture |
Yellow-green semen | Bacteria from a urinary infection leaking into the prostate | See a specialist promptly |
Normal appearance, abnormal culture | Many infections are invisible to the eye and only show up on testing | This is the most common pattern |
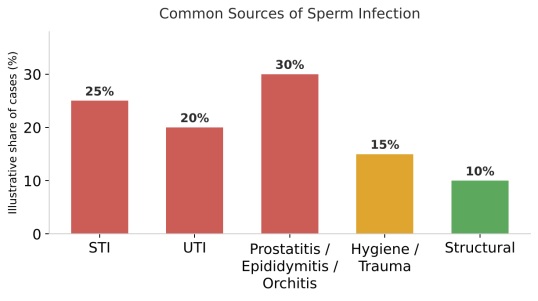
Chart 2 — Common Sources of Sperm Infection (illustrative)
Patient Example (anonymised)
“Patient K, 34, had a completely normal-looking semen sample on visual check but a semen culture flagged a UTI-linked bacterial count; a two-week antibiotic course and a repeat test three months later showed motility back in the normal range.”
— Composite of cases seen at FertilTree; details altered to protect patient identity.
Risk Factors, Organised by Type
Dozens of factors have been linked to sperm infection and broader sperm health in the research literature. Grouped by what you can actually do about each one, the list is far more useful than a single long bullet dump:
Category | Examples | What It Means |
Infection-related | Prior STIs or UTIs, prostatitis, epididymitis, orchitis, balanitis, mumps-related orchitis | Medical — needs treatment, not lifestyle change |
Structural / mechanical | Varicocele, obstructed ducts, undescended testicles, testicular torsion, vasectomy history | Medical — needs specialist evaluation |
Modifiable lifestyle | Smoking, excessive alcohol, illicit drug use, obesity, poor hygiene, unprotected sex, hot tub/sauna overuse, excessive cycling | Modifiable — within your control |
Medical / systemic | Uncontrolled diabetes, autoimmune conditions, chronic antibiotic use, chemotherapy or radiation, certain medications | Medical — manage the underlying condition |
Environmental / occupational | Heat or chemical exposure, certain occupations, excessive laptop/phone-on-lap heat exposure | Modifiable — reduce exposure where possible |
Symptoms: Why Are Most Infections Silent?
When a sperm infection does cause symptoms, they’re usually mild and easy to dismiss: discomfort, unusual discharge, or pain during ejaculation. The harder truth is that a large share of infections cause nothing noticeable at all — which is exactly why a semen analysis, not symptom-watching, is how most cases are actually found.
How Is a Sperm Infection Diagnosed?
Diagnosis starts with a standard semen analysis, paired with a semen culture that checks specifically for bacteria and an elevated white blood cell count. If a sexually transmitted cause is suspected, a urine or swab-based STI panel (chlamydia, gonorrhoea) is added. The oxidative stress that infection-linked white blood cells generate can also show up as elevated sperm DNA fragmentation or apoptosis, which some clinics test for separately when a cause isn’t obvious from the first round of testing.
The test itself has specific handling rules that affect whether the result is trustworthy, and most patient guides leave them out: semen pH above 7.2 and a white blood cell count above 1 million per millilitre are the standard thresholds for flagging infection-linked leukocytospermia; the sample needs 3-5 days of prior abstinence to be representative; and it should reach the lab within an hour of collection. A culture drawn outside these conditions — or taken while you’re partway through a self-started antibiotic course, as covered below — can read as falsely normal.
Can It Be Treated?
Yes, in most cases. Bacterial infections typically respond to a targeted antibiotic course, chosen based on the culture result rather than a guess — and your partner may need simultaneous treatment to prevent passing the infection back and forth. A repeat semen analysis after treatment is how you confirm it actually worked, both for the infection itself and for sperm parameters. Left untreated for long enough, chronic infection and the oxidative stress it causes can contribute to a measurable decline in sperm count — in some cases crossing into oligospermia or azoospermia territory — which is the main reason early testing matters more than waiting to see if symptoms appear.
Likely Cause | Typical Treatment | Partner Treatment Needed? | Recheck Window |
STI-related (chlamydia, gonorrhoea) | Targeted antibiotic course; partner treated simultaneously | Yes — essential | Re-test in 10-12 weeks |
UTI-linked bacterial infection | Culture-guided antibiotic course | Usually not required | Re-test in 10-12 weeks |
Prostatitis / epididymitis | Longer antibiotic course (often 2-4 weeks) + anti-inflammatory support | Not required | Re-test in 10-12 weeks, specialist follow-up |
Bacteriospermia, no clear source identified | Antibiotic choice guided by culture sensitivity; address modifiable risk factors alongside | Case-by-case | Re-test in 10-12 weeks |
One detail that explains a frustrating pattern — a cleared infection that still hasn’t fixed fertility — rarely makes it into general content: a genital tract infection can trigger the immune system to produce anti-sperm antibodies, which go on causing sperm to clump together and lose motility even after the bacteria themselves are gone. This is one reason a repeat semen analysis checks more than just whether the infection cleared; it’s also why some men need a longer recovery window than the antibiotic course alone would suggest.
Expert Insight — Dr. Firuza Parikh
“The patients who do best are the ones who get a semen culture early, before an infection has had months to cause oxidative damage — treating the bacteria is usually the easy part; it’s the delay that costs fertility.”
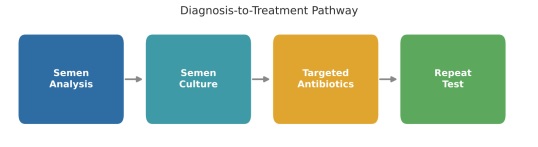
Chart 3 — Diagnosis-to-Treatment Pathway
The India-Specific Risk: Self-Medicating Before a Culture Is Done
There’s a specifically Indian wrinkle to this that most general fertility content misses entirely: pharmacy-counter antibiotics, bought without a prescription, are common enough to actively interfere with diagnosis. A 2024 community study from South-East Delhi, published in the Indian Journal of Community Medicine, found 35% of adults had self-medicated with antibiotics in the previous three months, 14% of those specifically for a urinary tract infection — and 75% got the antibiotic straight from a pharmacy, no prescription involved.
The problem isn’t just antibiotic resistance in the abstract. A short, incomplete course taken before a proper semen culture can suppress bacteria just enough to produce a false-negative result, while leaving the underlying infection — and the inflammation it’s causing — very much active. If you suspect a sperm infection, the single most useful thing you can do before any treatment is get a culture first, not a trip to the pharmacy counter.
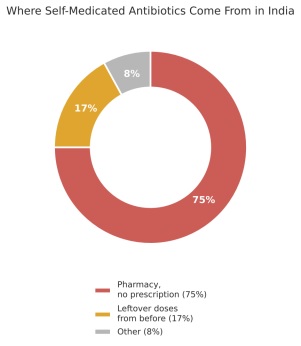
Chart 4 — Where Self-Medicated Antibiotics Come From (Delhi sample)
Prevention: What Actually Helps?
Prevention mostly maps onto the modifiable-risk-factor row in the table above: practising safe sex, treating UTIs promptly instead of waiting them out, maintaining good genital hygiene, and avoiding prolonged heat exposure to the testicles. A male infertility specialist can also advise on diet and lifestyle changes that support sperm health generally, which compounds with infection prevention rather than replacing it.
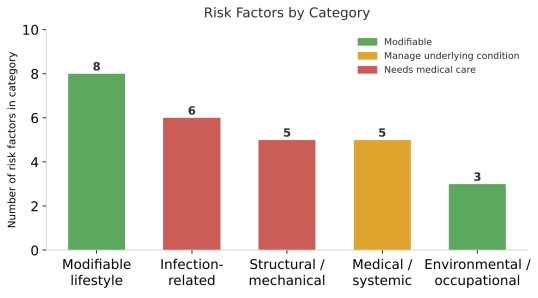
Chart 5 — Risk Factors by Category
Questions Patients Actually Ask
Does having bacteria in semen always mean I have an infection?
Not necessarily. A low level of bacteria (bacteriospermia) without a raised white-blood-cell count or symptoms is sometimes incidental — your specialist interprets the full culture result, not just “bacteria: yes/no.”
Can this spread to my partner?
If the cause is an STI, yes — which is exactly why partner treatment is usually recommended alongside your own, even if your partner has no symptoms.
How long before a repeat test actually means something?
Most clinics wait at least 10–12 weeks after treatment, since that’s roughly how long a full sperm production cycle takes — testing earlier can show lingering effects that aren’t about the infection anymore.
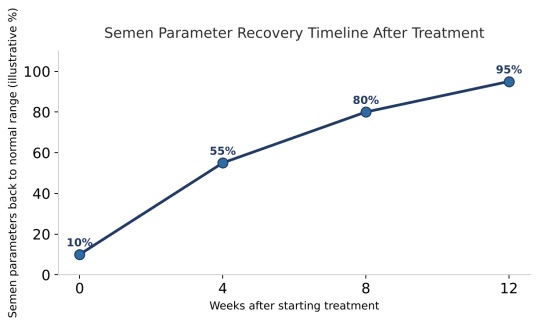
Chart 6 — Recovery Timeline After Treatment
Bottom line
A sperm infection is common, usually silent, and usually treatable. Roughly 15% of male infertility involves one, almost always starting as a UTI, an STI, or inflammation in the prostate or epididymis. A semen culture, not symptom-watching, is how it’s actually found — and most bacterial cases clear with the right antibiotic course.
Frequently Asked Questions
Can an infection in sperm be treated?
Yes. Most bacterial sperm infections clear with a targeted course of antibiotics, often alongside treatment for your partner to prevent re-infection. Viral causes are managed rather than cured, and a repeat semen analysis after treatment confirms whether sperm parameters have recovered.
Does an infection in sperm always lead to infertility?
No. Many men with a mild or promptly treated infection have no lasting fertility impact. The risk rises with how long the infection goes untreated, since it’s the prolonged inflammation and oxidative stress — not the infection’s first days — that damage sperm function over time.
How is an infection in sperm diagnosed?
Through a semen analysis combined with a semen culture, which checks for bacteria and an elevated white blood cell count. If a sexually transmitted infection is suspected, a urine or swab-based STI panel is added. See what a semen analysis involves and costs for the specifics of the first-step test.
Can FertilTree help with fertility issues related to a sperm infection?
Yes. FertilTree’s male fertility evaluation includes semen culture and STI testing alongside a standard semen analysis, with treatment coordinated between urology and the fertility team before any assisted reproduction is considered.
MEDICALLY REVIEWED BY
Dr. Firuza Parikh
MD, PhD, Director, Jaslok-FertilTree International Fertility Centre
Male fertility evaluations at FertilTree routinely include a semen culture alongside the standard semen analysis, specifically to catch the infections that cause no symptoms at all. Dr. Parikh trained at KEM Hospital, Seth G.S. Medical College and Nowrosjee Wadia Maternity Hospital, Mumbai, before completing fellowship training in IVF and Reproductive Endocrinology at Yale University School of Medicine under Dr. Alan DeCherney. She returned to India in 1989 to establish one of the country’s first private-hospital IVF centres at Jaslok Hospital, and in 1994 her team delivered South-East Asia’s first ICSI baby. Over more than three decades in reproductive medicine, she and her team have helped deliver more than 20,000 babies for patients from over 60 countries.